STAND-ALONE BEDSIDE PROCEDURE PATHWAY
Abdominal paracentesis
Ultrasound-selected diagnostic tap or controlled large-volume drainage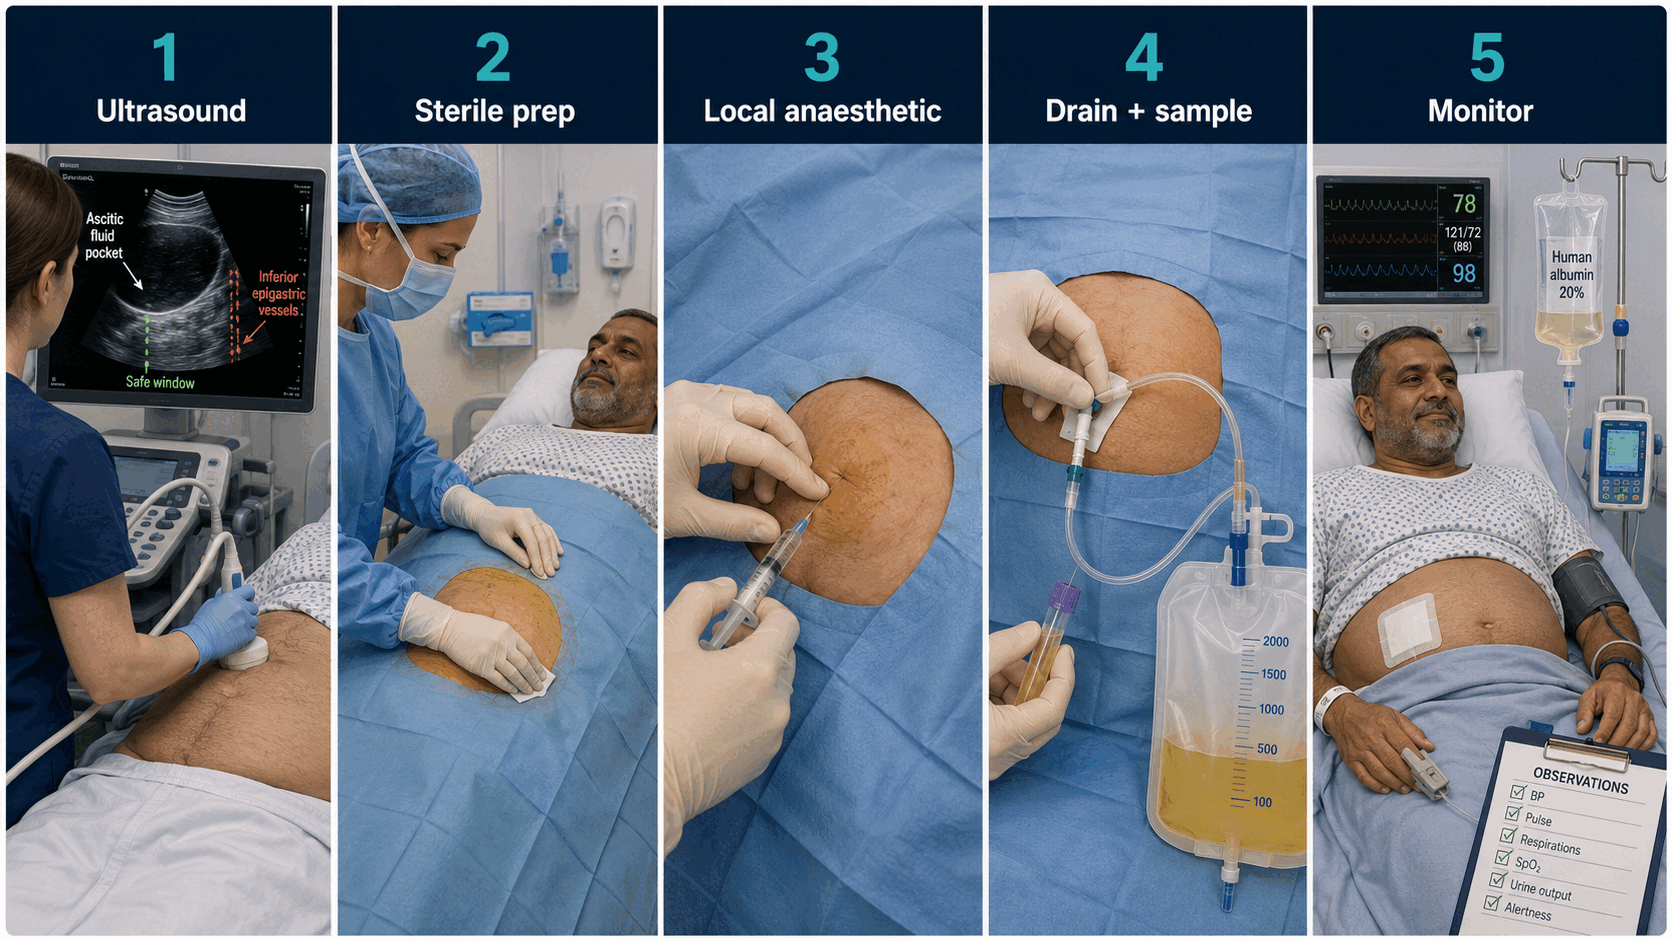
Indications
- New ascites, hospital admission with cirrhosis or clinical deterioration
- Suspected spontaneous bacterial peritonitis
- Tense/symptomatic or malignant ascites requiring therapeutic drainage
Stop / escalate
- No safe pocket or uncertain anatomy—use ultrasound/expert operator
- DIC or clinically significant bleeding risk requires individual correction plan
- Acute abdomen, loculation, pregnancy or organomegaly changes site/operator strategy
Illustrated step sequence
Samples / technical essentials
- Cell count with neutrophils—PMN ≥250 cells/mm³ supports SBP treatment
- Albumin and paired serum albumin for SAAG; total protein
- Bedside inoculation into aerobic/anaerobic blood-culture bottles; cytology/other tests by phenotype
Aftercare and complications
- Albumin: 8 g per litre removed when >5 L drained; consider with smaller volumes if high AKI risk per specialist guidance
- Monitor BP, pain, leakage, bleeding, renal function and sodium
- Escalate peritonism, haemorrhage, persistent leak, hypotension or AKI
Supervised clinician education. Use the current local checklist, competency standard, consent policy, infection-control procedure and escalation route. This pathway does not certify procedural competence.